
Hip Pain: Causes, Diagnosis, and Treatment
How a pain specialist looks beyond arthritis when diagnosing hip pain
Hip pain has more than one cause. Where you feel it, when it flares, and what makes it worse can tell us a lot about where the pain is coming from, often revealing clues beyond what’s visible on a scan.
Medically reviewed by Dr Nick Christelis, FFPMANZCA, Medical Director Pain Specialists Australia | Last updated: August 2026
What you need to know
Hip pain is not always arthritis. Common causes also include gluteal tendinopathy, greater trochanteric pain syndrome (GTPS), hip labral tears, femoroacetabular impingement, iliopsoas tendinopathy, and pain referred from the lower back.
Where you feel hip pain often points to what is causing it. Front, side, back, and deep hip pain each suggest different causes.
A normal X-ray or MRI does not rule out real hip pain. Many hip conditions are diagnosed clinically, not on imaging alone.
Steroid (Cortisone) injections that only last a few weeks, or physiotherapy that doesn’t help, usually means the diagnosis is incomplete rather than the treatment is failing.
If your hip pain has not resolved after three to six months of first-line care, a specialist pain assessment can help with the diagnosis and treatment plan.
Where you feel hip pain and what it usually means
The location of hip pain is the single most useful diagnostic step. At Pain Specialists Australia, it is the first thing we aim to understand during a Melbourne hip pain assessment.
Use the guide below to work out where your pain is. The possible causes and next steps are listed under each zone.
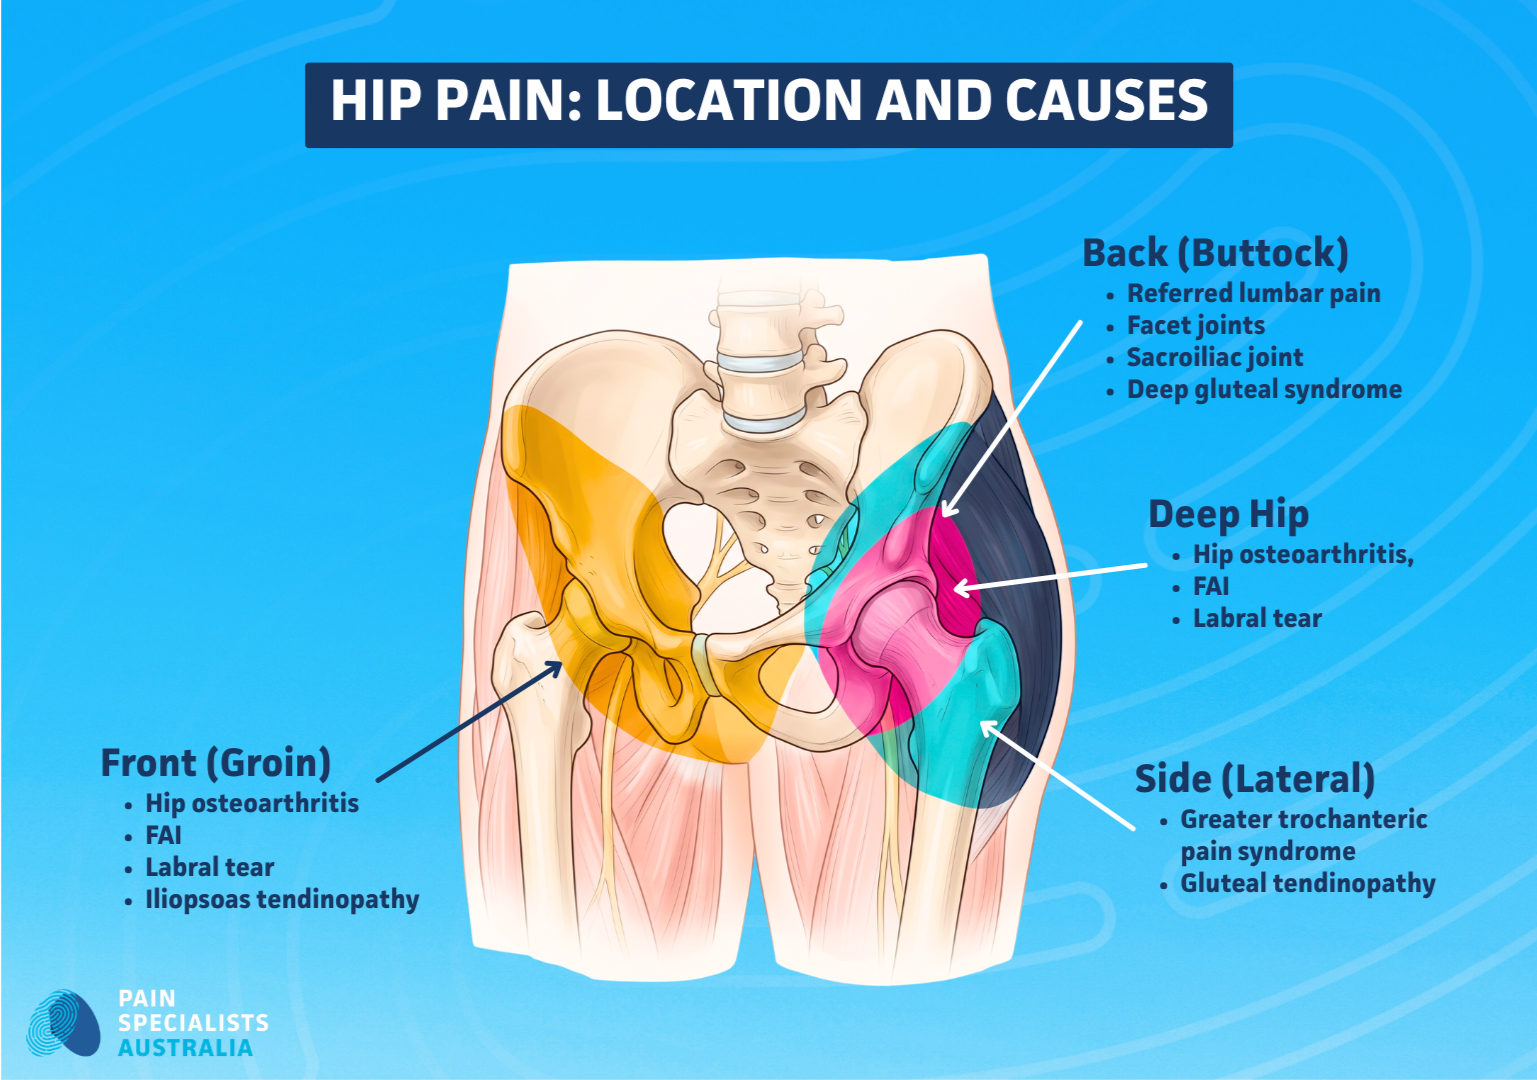
Where you feel hip pain often points to what's causing it. Pain specialists use this map to guide diagnosis.
Pain in the front of the hip or groin
Pain in the groin or front of the hip usually points to problems inside the hip joint itself like
Hip osteoarthritis
Femoroacetabular impingement (FAI)
Hip labral tears
Iliopsoas tendinopathy
It often flares when getting out of a low chair or a car.
Pain on the outside of the hip (lateral hip pain)
Pain over the bony point on the outside of the hip is one of the most recognisable patterns in hip pain. This is usually greater trochanteric pain syndrome and gluteal tendinopathy rather than the older diagnosis of trochanteric bursitis.
This usually causes pain when lying on that side at night.
Before one can get the right treatment, you need the right diagnosis.
Pain deep inside the hip joint
A deep ache that seems to sit inside the joint often reflects true intra-articular pathology. Common causes include:
Osteoarthritis
Labral tears
FAI.
Patients sometimes describe it by making a C-shape with the thumb and fingers around the hip. This pattern is so recognisable it has a clinical name: the C-sign.
Pain in the back of the hip or buttock
Pain felt in the buttock or the back of the hip may not be coming from the hip joint at all.
Common sources include:
The lumbar spine like the lumbar facet joints
The sacroiliac joint
The piriformis and other deep gluteal muscles
Cluneal nerve entrapments.
Hip pain radiating down the leg
Pain that starts near the hip and travels down the leg suggests a nerve or referred pain. This is often called lumbar radicular pain, but it can also be due to sciatic irritation in the deep gluteal region.
Hip Osteoarthritis
Hip osteoarthritis is wear of the cartilage lining the ball-and-socket joint. It typically presents in adults over 50 with symptoms including:
Groin and front-of-thigh pain
Morning stiffness that eases within about 30 minutes
Difficulty putting on socks or shoes.
Plain X-ray usually shows joint space narrowing. Remember, many people may have hip osteoarthritis but not feel any hip pain. The severity of the X-ray and the severity of the pain do not always match.
Understand where your hip pain is coming from
Common causes of hip pain that get missed
Osteoarthritis is common. It is also over-diagnosed. Many patients who are told they have "hip arthritis" actually have gluteal tendinopathy, iliopsoas tendinopathy, pain referred from the spine or other causes of the pain.
The conditions below are the ones most often missed or misdiagnosed.
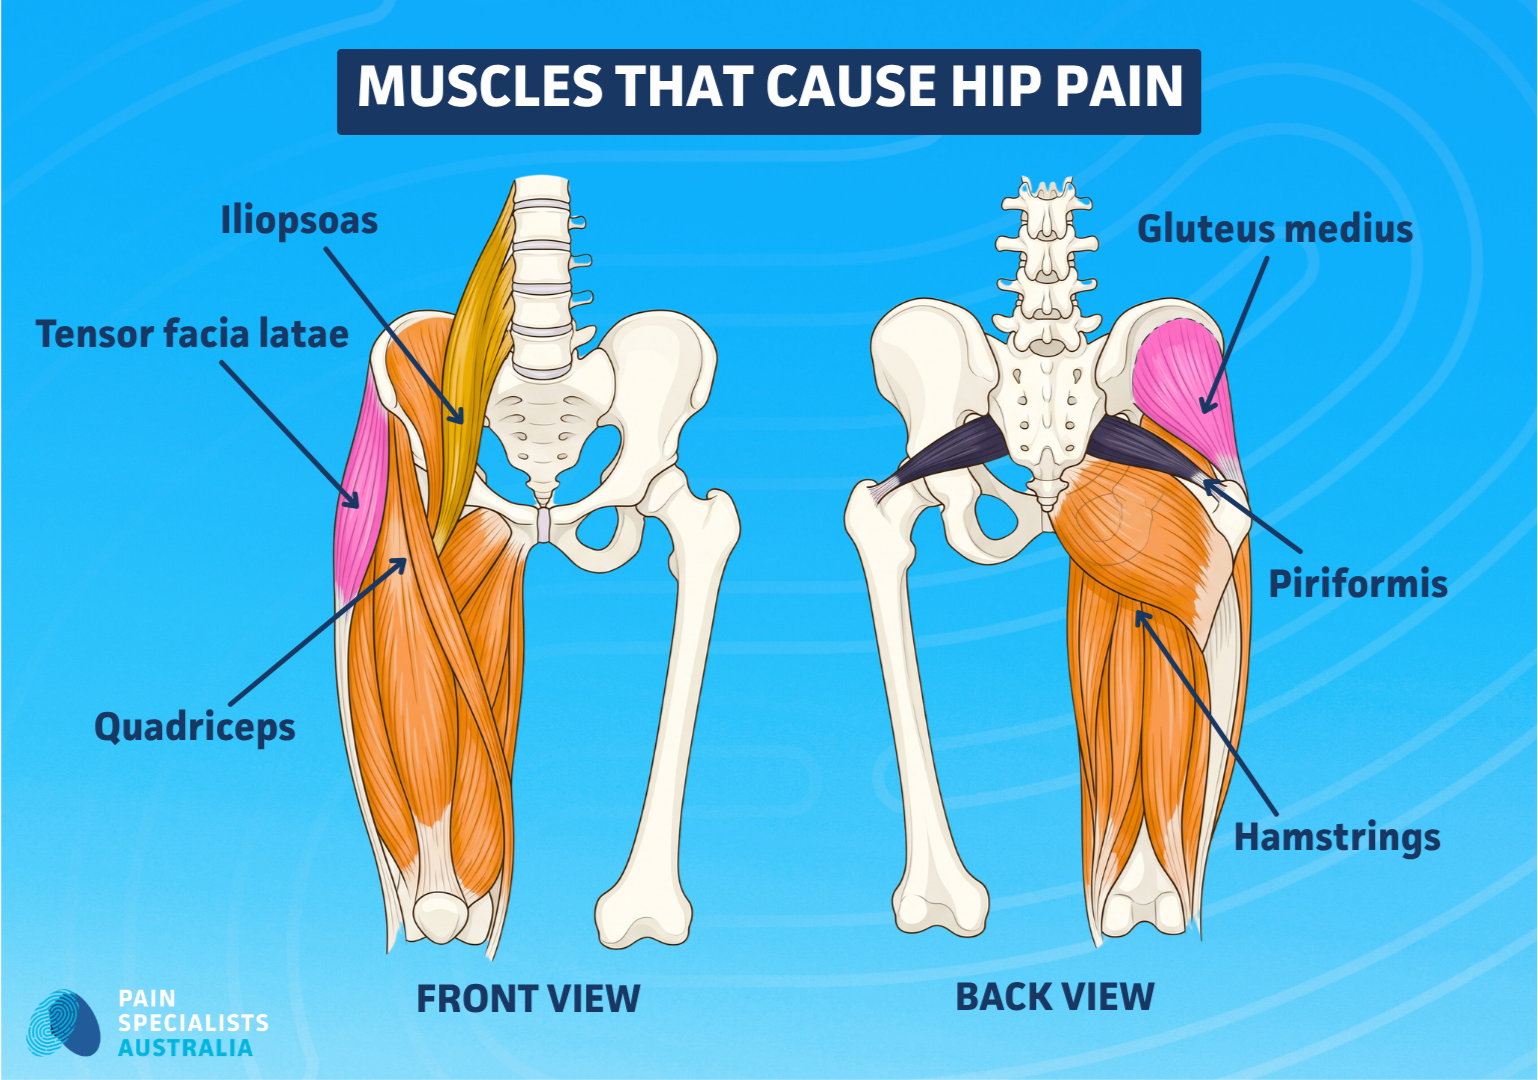
The main muscles that cause hip pain, front and back views.
Greater trochanteric pain syndrome and gluteal tendinopathy
Greater trochanteric pain syndrome (GTPS) is pain over the outside of the hip. It is most often caused by gluteal tendinopathy: wear and irritation of the tendons of the gluteus medius and gluteus minimus.
The classic pain pattern is sharp or burning pain that wakes patients when they lie on that side. Historically, this was called trochanteric bursitis and treated with repeated cortisone injections. Current research shows the tendon is usually the primary source of pain.
Clinical observation: patients who have had three or more bursae cortisone injections without lasting benefit usually have a gluteal tendinopathy that needs a different treatment strategy, not another cortisone injection.
Hip labral tears
The labrum is a ring of cartilage around the rim of the hip socket. Labral tears typically present in younger, active adults with anterior hip or groin pain, clicking, and pain with hip flexion and rotation.
Labral tears are also frequently seen on MRI in people with no hip pain at all. This means a labral tear on your scan is not necessarily the source of your pain.
Femoroacetabular impingement (FAI)
FAI is a mismatch in the shape of the ball or socket, causing them to pinch during certain movements. It typically presents in active adults under 50 with groin pain that worsens with prolonged sitting, deep hip flexion, or twisting.
FAI often coexists with labral tears. Not everyone with extra bone growth on scans has FAI symptoms.
Iliopsoas tendinopathy (psoas syndrome)
The iliopsoas is the main hip flexor (lifts your thigh upwards), running deep in the front of the hip. Iliopsoas tendinopathy causes pain in the front of the hip and groin, often with a distinctive worsening when rising from a low chair.
It is commonly missed on standard imaging. It is one of the most common causes of anterior hip pain misdiagnosed as osteoarthritis.
Hip pain referred from the lower back or sacroiliac joint
The lumbar spine, sacroiliac joint, and pelvic structures share nerves with the hip region. Pain referred from the lower back can present as hip pain.
This overlap explains why patients are sometimes sent for hip imaging that comes back normal. The pain is coming from the spine.
Nerve-related hip pain
Nerves around the hip can produce burning, shooting, or electric pain patterns. Common examples include:
Lateral femoral cutaneous nerve irritation (also called meralgia paraesthetica),
Cluneal nerve entrapment, and
Post-surgical nerve sensitivity – nerve pain triggered by surgery
Clinical observation: if hip pain includes burning, tingling, sensitivity to light touch, or an electric-shock-like quality, it is often a nerve pain rather than a joint pain.
Pain after hip replacement
Persistent pain after hip replacement is less common than after knee replacement but it can occur. When it does occur, the source is usually not the hip replacement itself i.e. the hardware.
The more common causes of chronic pain after hip replacment are:
Nerve injury,
Gluteal tendinopathy that was present before surgery and never addressed,
Iliopsoas irritation from a prominent implant, or
Centrally sensitised pain patterns.
Remember that if you have chronic pain after a hip replacement, your surgeon will need to assess you for surgical complications like infections, or prosthetic issues.
Dr Nick Christelis and a Melbourne-based hip surgeon discuss chronic pain after hip replacement surgery in this episode of our video podcast.
Hip pain symptoms: the patterns that point to a diagnosis
The timing of your hip pain can help with the diagnosis. Different time patterns suggest different causes.
When hip pain is worse at night
Night pain that wakes you lying on the affected side is the classic pattern for gluteal tendinopathy and GTPS. It happens because the tendons push against the greater trochanter when you lie on that side.
When hip pain flares after sitting
Pain that flares after prolonged sitting, and then eases with movement, can occur in:
FAI and
intra-articular hip pathology.
It happens because the hip is held in a flexed position, while sitting, that loads the anterior joint structures i.e. front of the hip.
When hip pain hurts getting up from a chair
Pain in the front of the hip or groin when rising from a low chair is a classic pattern for:
iliopsoas tendinopathy or
intra-articular hip pathology.
That movement puts pressure on the front (anterior) hip structures.
When hip pain wakes you lying on that side
Sharp or burning pain over the outside of the hip when you roll onto that side almost always signals greater trochanteric pain syndrome.
Cortisone injections may help briefly, but a specific loading program is usually what actually resolves it.
Why scans can be normal when the pain is real
One of the most common frustrations we hear from Melbourne patients is that their scan came back normal, but their pain hasn't changed. A normal scan does not rule out real hip pain.
Plain X-ray shows bone. It doesn't show tendons, ligaments, nerves, or the joint capsule. Gluteal tendinopathy, iliopsoas tendinopathy, and nerve-mediated pain usually don't show up on an X-ray, even when severe.
MRI shows structure but doesn't show pain. Studies of people with no hip pain have found high rates of labral tears and cartilage abnormalities. Structure and symptoms don't always match.
Many hip conditions are clinical diagnoses. The examination, the pattern of symptoms, and sometimes a targeted diagnostic injection are more informative than the scan report.
If you have been told "the scan is normal" and your pain has not gone away, the scan hasn't helped with the diagnosis.
How our Melbourne pain specialists diagnose hip pain
Pain specialists approach hip pain diagnostically before therapeutically i.e. it is best to make the correct diagnosis first before the right treatment can be applied.
The goal of the first appointment is to identify what is actually causing the pain.
The clinical history: what a pain specialist listens for
The assessment starts with a detailed history. When the pain started, how it began, where it is felt, what makes it better or worse, and what has been tried.
This part often takes 15 to 20 minutes. It identifies the likely source in most cases before any examination is done.
The physical examination: what a scan cannot show
The examination confirms or defines the working diagnosis. Specific tests are used depending on which cause is being considered.
Some examinations movements might include:
Feeling (palpation) over the greater trochanter and single-leg stance testing for GTPS.
Hip flexion and rotation maneuvers for FAI and labral tears.
Resisted hip flexion for iliopsoas tendinopathy.
Assessment of the lumbar spine and sacroiliac joint for referred contributors.
When imaging helps, and when it misleads
Imaging is ordered only when needed.
Plain X-ray is useful for osteoarthritis and structural anatomy.
MRI is useful for cartilage, labrum, tendon, and marrow.
Ultrasound is useful for real-time assessment of gluteal tendons and iliopsoas.
In many cases, imaging confirms what the examination has already identified. It is not usually used to find the diagnosis.
Diagnostic injections as a diagnostic tool
Image-guided injections is a good diagnostic tool in hip pain assessment. A small amount of local anaesthetic is placed precisely onto or into a specific structure temporarily relieves pain from that structure.
If the pain reduces for the duration of the local anaesthetic or longer, that structure is likely to be confirmed as a cause of the pain. If it doesn't reduce, alternative structures may be considered.
Hip pain treatment: What actually works and when
Treatment is chosen based on what is generating the pain, how long it has been present, and what has already been tried.
There is no single treatment that works for all hip pain.
First-line treatment and physiotherapy
For most acute and early chronic hip pain, first-line treatment includes:
Activity modification and appropriate loading of the muscle, not complete rest
Structured physiotherapy targeted at the specific condition
Simple pain medications where needed
For gluteal tendinopathy, the loading strategy is what matters most. The LEAP trial (BMJ 2018) showed education plus an appropriate loading program produces better outcomes than either cortisone or a wait-and-see approach.
Medications for hip pain
Medications are chosen to match the underlying mechanism:
Simple analgesics for mild-to-moderate pain
Anti-inflammatories where appropriate and safe
Neuropathic (nerve) pain medications where nerve-pain is present
Muscle relaxants for muscle spasm-related pain
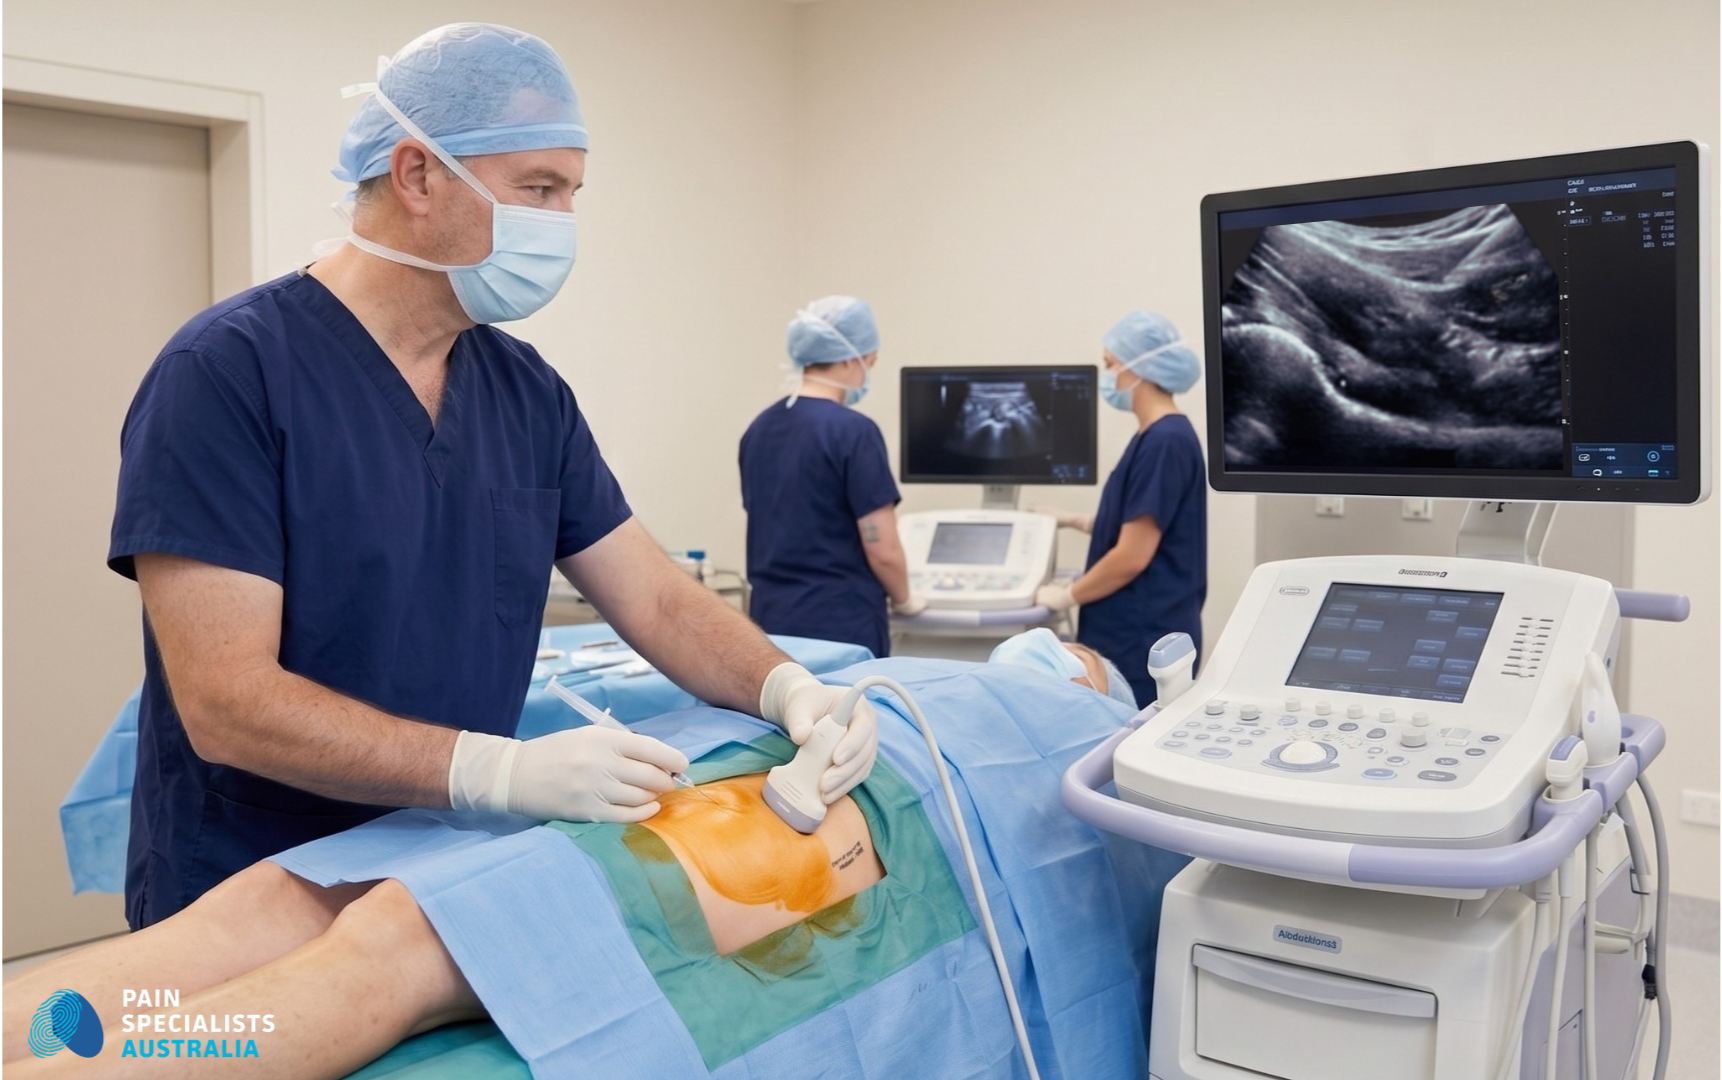
Image-guided injections of the articular branches of the femoral and obturator nerves can reduce hip osteoarthritis pain, particularly for patients not ready for or unable to have joint replacement.
Image-guided hip injections
Image-guided hip injections can help with the diagnosis or treatment or, or both. Options include:
Intra-articular hip joint injections – injections into the hip joint
Greater trochanteric or gluteal peritendinous injections – injections into or around the muscles and tendons on the side of the hip
Iliopsoas bursa or tendon sheath injections - injections into or around the muscles and tendons in the front of the hip
Facet joint injections – injections into the facet joints of the lower back
Sacroiliac joint injections – injections into the pelvic joint at the back
Nerve blocks (in lateral femoral cutaneous nerve, cluneal nerves, articular branches of the femoral and obturator nerves) - injections onto some nearby and surrounding nerves
Radiofrequency ablation and pulsed radiofrequency
When a specific nerve or joint is confirmed as a pain source through diagnostic injections (blocks), then radiofrequency ablation can be used to modulate the pain for a longer period of time.
In the hip, radiofrequency ablation is most commonly performed on the articular branches of the femoral and obturator nerves i.e. the nerves to the hip joint. It is often used for hip joint osteoarthritis pain in patients who are not surgical candidates or who want to defer surgery or are too unwell for surgery.
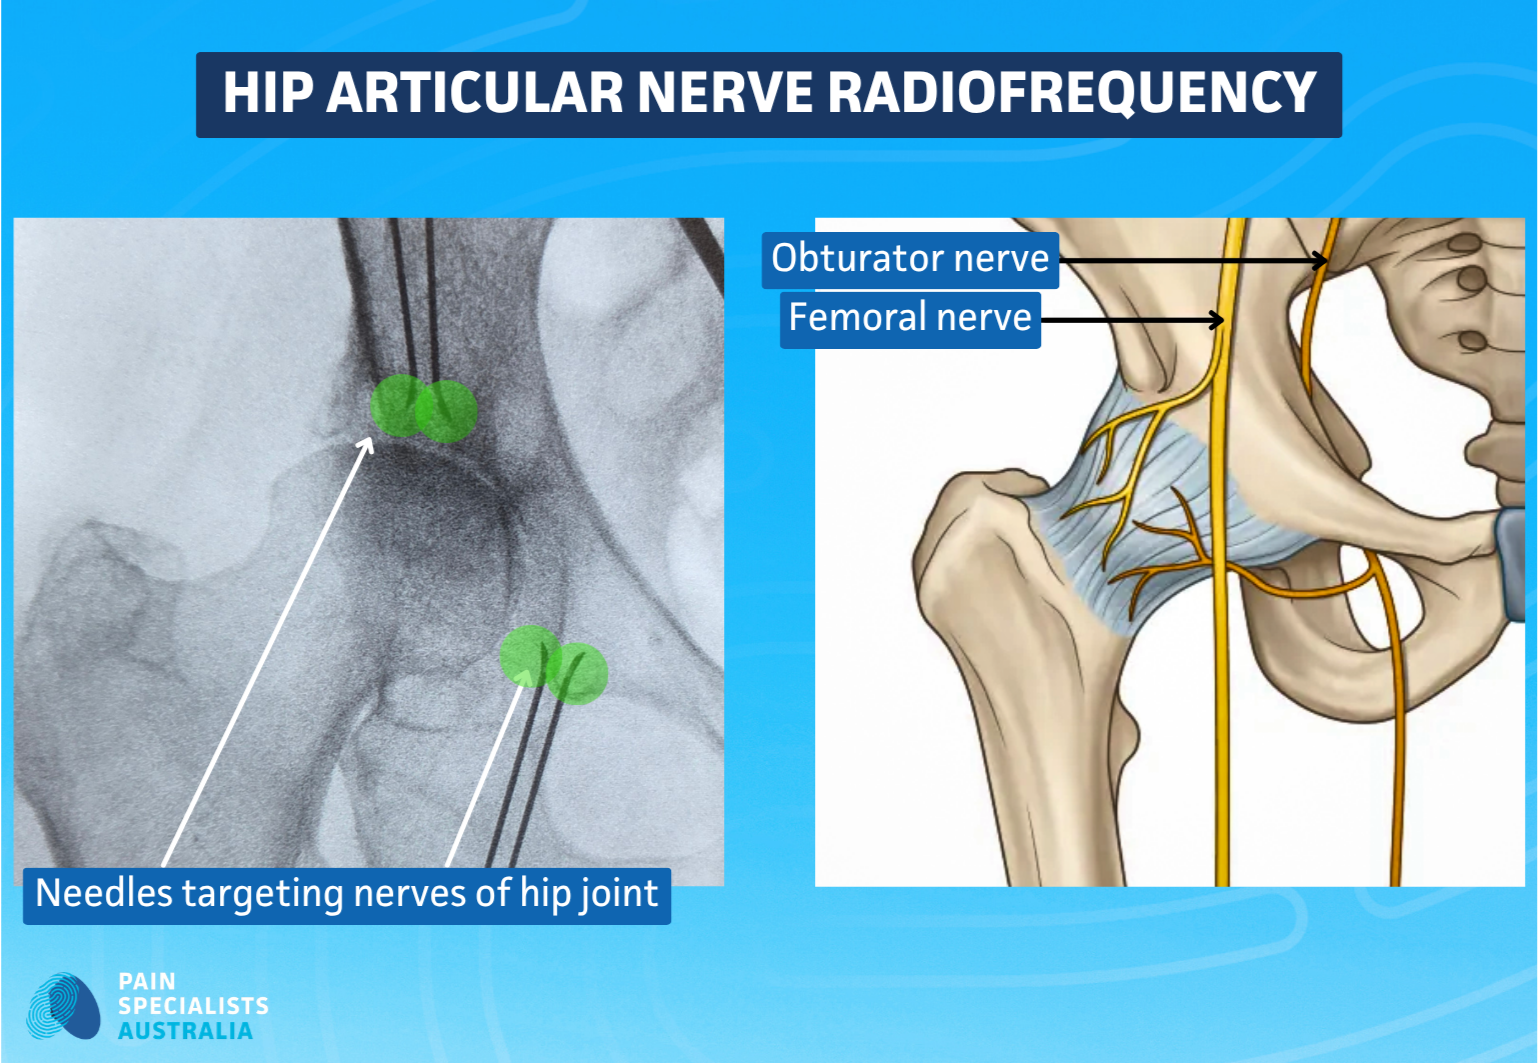
Radiofrequency ablation of the hip articular nerves can provide longer-term pain relief for hip pain.
Platelet-rich plasma (PRP) for hip tendinopathy
PRP injections are used in selected cases of gluteal tendinopathy and other tendon-based hip conditions. The research for this treatment is evolving.
PRP is not a first-line treatment but can be useful for the right patient after appropriate diagnostic workup.
Neuromodulation for severe chronic hip pain
For a small subset of patients with severe hip pain that has not responded to structured conservative and interventional care, and surgery has been performed or is not indicted, advanced pain strategies might be considered.
These are highly selective treatments used only in certain circumstances.
When surgery is and isn't the answer
Hip replacement, hip arthroscopy, and other surgical procedures have clear roles in specific patient groups. These are best discussed with your hip surgeon. We work closely with hip surgeons when needed.
Where structural pathology matches symptoms and conservative care has been trialled and failed, then surgery should be considered.
Where the diagnostic picture is unclear, or where nerve pain and centrally sensitised components are prominent, surgery may not be the right first step.
A pain specialist assessment can sometimes help clarify whether surgical referral is appropriate.
When physiotherapy stops working: What comes next
Physiotherapy is a foundational treatment for most hip pain conditions. When it stops working, there are usually two reasons.
1. The most common reason physio doesn’t work is that the diagnosis was incomplete, so the exercise and loading strategy didn't match the underlying diagnosis.
Gluteal tendinopathy treated with the wrong exercise program can worsen rather than improve the pain. If referred pain from the spine is treated as hip pain, it will not respond, regardless of how good the physiotherapy is.
2. The other reason physiotherapy may fail is that the physio targets the hip and surrounding area, but it doesn’t target a contributing factor like pelvic muscles, spinal pain or central sensitisation nerve pain, which may need to be directly focused on.
If you have completed three to six months of structured physiotherapy without meaningful improvement, a pain specialist assessment can help revisit the diagnosis and plan a coordinated next phase.
What people describe in our Melbourne clinics
We listen closely to what people with hip pain share in our Melbourne clinics and in online communities.
Common complaints we read and hear include:
Being told the pain is "just arthritis" when the diagnosis is not arthritis
Sharp or aching pain on the outside of the hip that makes it impossible to sleep on that side
Deep groin pain that flares when getting out of a car or a low chair
A scan that came back normal despite significant pain and loss of function
Cortisone injections that helped briefly but stopped lasting after two or three rounds
Physiotherapy that helped for a while, then plateaued or the pain came back
Not knowing whether the pain is coming from the hip, the lower back, or both
Feeling too young for a hip replacement and not knowing what other options exist
Getting a different explanation from every clinician seen.
Warning signs that need urgent assessment
Most hip pain is not dangerous. Some patterns need urgent medical review. Seek prompt assessment if you experience:
Sudden, severe, disabling hip pain, particularly after a fall or injury
Inability to weight-bear or walk on the affected leg
Fever, sweats, or feeling unwell alongside hip pain
The hip area is red, hot, or swollen
Unexplained weight loss or night pain that is rapidly worsening
New numbness, weakness, or tingling in the leg
Changes in bladder or bowel function alongside back or hip pain
Hip pain in a child or adolescent, particularly with limping.


Frequently Asked Questions (FAQ)
1. Why does the outside of my hip hurt when I lie on it?
Pain on the outside of the hip that worsens when lying on that side is the classic presentation of greater trochanteric pain syndrome, usually caused by gluteal tendinopathy.
It happens because the tendons attaching the gluteal muscles are compressed and irritated when the joint is loaded from the side. Getting the diagnosis right matters because gluteal tendinopathy responds to a specific loading program and sometimes PRP injections rather than repeated cortisone injections.
2. Can I have hip pain if my scans are normal?
Yes. Causes of hip pain, including gluteal tendinopathy, iliopsoas tendinopathy, nerve-mediated pain, and pain referred from the lower back, do not always show up on X-ray and may not be detected on MRI.
Diagnosis for these conditions relies on clinical history, examination, and sometimes scans with consideration for targeted diagnostic injections rather than relying on imaging alone.
3. Why is my hip pain worse at night?
Night pain that wakes you lying on the affected side is most often greater trochanteric pain syndrome, though it can also occur with inflammatory arthritis or advanced osteoarthritis.
It happens because pressure on the outside of the hip loads (puts pressure on) the gluteal tendons, or because hip joint inflammation becomes stiffer at rest.
Persistent night pain that is rapidly worsening warrants prompt assessment to rule out less common but more serious causes.
4. Is my hip pain coming from my hip or my lower back?
Both are possible, and both can happen at the same time.
Pain in the buttock or back of the hip can be referred from the lumbar spine or sacroiliac joint, while pain in the groin or deep in the hip joint usually reflects a true hip source.
A specialist assessment can identify which structures are contributing and in what proportion, which matters because treating the wrong site will not help.
5. Why hasn't cortisone worked for my hip pain?
Cortisone can provide short-term relief for some hip conditions but often does not address the underlying cause. In gluteal tendinopathy, for example, cortisone may give brief relief while the tendon itself continues to deteriorate.
Repeated cortisone injections that don't provide lasting benefit are usually a signal that the diagnosis needs to be revisited.
6. What's the difference between hip bursitis and gluteal tendinopathy?
The older label of "trochanteric or hip bursitis" assumed the pain came from an inflamed bursa on the outside of the hip. Current evidence shows the tendons of the gluteal muscles are usually the main source of the pain in most cases, with any bursa inflammation usually occur as a consequence.
This matters because bursitis and tendinopathy have different treatments, and the wrong diagnosis may lead to the wrong treatments.
7. What does a hip labral tear feel like?
A hip labral tear typically feels like:
Front (anterior) hip or groin pain, with
Clicking or catching sensations, and
Pain with hip flexion and rotation.
Getting in and out of the car is usually painful. Labral tears also appear on MRI in people with no hip pain, so a diagnostic examination and sometimes an intra-articular injection are more useful than the MRI report alone.
8. Do I need a hip replacement if I have hip osteoarthritis?
Not always. Hip replacement is a highly effective operation for advanced hip osteoarthritis in the right patient, but many people with hip osteoarthritis can be well managed with a combination of conservative care, targeted injections, and specialist pain management.
The decision depends on symptom severity, functional impact, response to non-surgical management, and individual patient factors.
9. What happens at a pain specialist appointment for hip pain?
A pain specialist appointment for hip pain begins with a detailed history, followed by a targeted physical examination. Existing imaging is reviewed, and further imaging or a diagnostic injection may be recommended if needed.
The goal of the first appointment is to make a diagnosis and only then can the right treatment(s) be considered.
10. How long should I try physiotherapy before seeing a pain specialist?
For most hip pain conditions, three to six months of physiotherapy is a reasonable trial.
If your pain has not improved meaningfully in that time, or if it improved then plateaued or returned, a pain specialist assessment can help identify whether the diagnosis was complete and whether targeted procedures might be appropriate alongside continued rehabilitation.
References
1. Wilson JJ, Furukawa M. Evaluation of the patient with hip pain. American Family Physician. 2014;89(1):27-34.
A medical guide for doctors showing how the location of hip pain, whether at the front, side, or back, points to different underlying causes. This is the framework behind the location-based diagnostic map used on this page.
https://pubmed.ncbi.nlm.nih.gov/24444505/
2. Mellor R, Bennell K, Grimaldi A, et al. Education plus exercise versus corticosteroid injection use versus a wait and see approach on global outcome and pain from gluteal tendinopathy (LEAP trial). BMJ. 2018;361:k1662.
A large Australian trial comparing three treatments for pain on the outside of the hip: a structured education and exercise program, cortisone injections, or a wait-and-see approach. The exercise and education program worked better than cortisone.
https://pubmed.ncbi.nlm.nih.gov/29720374/
3. Griffin DR, Dickenson EJ, Wall PDH, et al. Hip arthroscopy versus best conservative care for the treatment of femoroacetabular impingement syndrome (UK FASHIoN): a multicentre randomised controlled trial. The Lancet. 2018;391(10136):2225-2235.
A major UK trial comparing keyhole hip surgery with a structured physiotherapy program for people with femoroacetabular impingement (FAI), a hip shape problem that causes pinching pain during movement. Helps guide who is likely to benefit from surgery and who is not.
https://pubmed.ncbi.nlm.nih.gov/29893223/
4. Griffin DR, Dickenson EJ, O'Donnell J, et al. The Warwick Agreement on femoroacetabular impingement syndrome: an international consensus statement. British Journal of Sports Medicine. 2016;50(19):1169-1176.
A worldwide agreement among hip experts stating that FAI can only be diagnosed when a person has all three of: symptoms, physical examination findings, and matching scan findings. A scan alone is not enough to make the diagnosis.
https://pubmed.ncbi.nlm.nih.gov/27629403/
5. Register B, Pennock AT, Ho CP, et al. Prevalence of abnormal hip findings in asymptomatic participants: a prospective, blinded study. American Journal of Sports Medicine. 2012;40(12):2720-2724.
A study that scanned the hips of people with no hip pain at all and found labral tears in 69% of them, alongside many other abnormalities. This is the evidence behind why a labral tear or other finding on your scan does not automatically mean it is the source of your pain.
https://pubmed.ncbi.nlm.nih.gov/23104610/
6. Grimaldi A, Fearon A. Gluteal tendinopathy: integrating pathomechanics and clinical features in its management. Journal of Orthopaedic and Sports Physical Therapy. 2015;45(11):910-922.
A specialist review explaining why what was traditionally called "trochanteric bursitis" is now understood to be gluteal tendinopathy (a tendon problem), and how that changes what treatment actually works.
https://pubmed.ncbi.nlm.nih.gov/26381486/
7. Bannuru RR, Osani MC, Vaysbrot EE, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589.
The current international guidelines for managing hip osteoarthritis without surgery. Covers exercise, education, weight management, and medications, and helps guide the treatment ladder for people not ready for joint replacement.
https://pubmed.ncbi.nlm.nih.gov/31278997/
8. Kapural L, Jolly S, Mantoan J, et al. Cooled radiofrequency neurotomy of the articular sensory branches of the obturator and femoral nerves: combined approach using fluoroscopy and ultrasound guidance. Pain Physician. 2018;21(3):279-284.
Research showing that radiofrequency treatment of the specific nerves that supply the hip joint (the femoral and obturator articular branches) is safe and can reduce chronic hip pain, particularly for people who are not surgical candidates or want to delay joint replacement.
